
This article is penned down by DentalReach Dental Divas Summit (DRDDS) 3 Speaker Dr Disha Gupta. Dr Disha is practicing in Dubai (UAE ) as a microscopic endodontist for 8 years. If you wish to associate with DentalReach or Dental Divas, please get in touch with me - editor@dentalreach.co 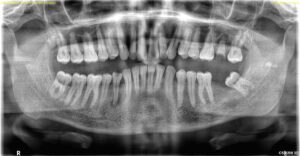 Close look
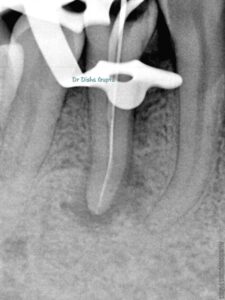 A lateral lesion also signified presence of extra canal or lateral canal.
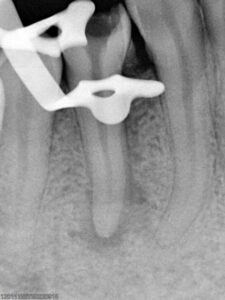
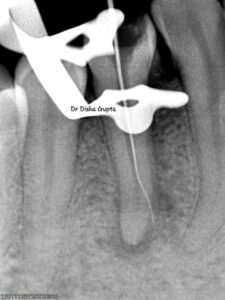
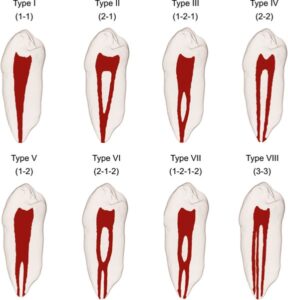
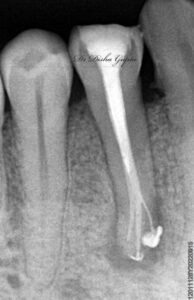
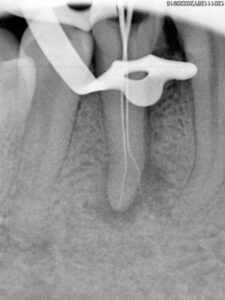 Type V root canal configuration was seen with the buccal canal.
Abstract
Mandibular first premolars usually have a one root and one root canal but it shows a wide variety of abnormal root canal anatomy. Especially, the occurrence of three canals with deep apical split in mandibular first premolars is very rare, but it does occur. The incidence of a three-canaled mandibular first premolar is approximately 0.2%, making such teeth most difficult to manage endodontically. Knowledge of root canal morphology, proper radiographic interpretation, Cone beam CT scan interpretation, use of magnification in terms of dental operating microscope, and scouting of the root canals are important in detecting the presence of the multiple canals. This case report presents a comprehensive approach to successfully treating mandibular 1st premolar with deep split. Keywords: anomaly, mandibular premolars, root canal, deep split, endodonticsCase Report
A 35-year-old male patient presented to the dental clinic with chief complaint of severe spontaneous pain in the mandibular right premolar region. Clinical examination and radiographic evaluation revealed deep caries with carious exposure. Tenderness was positive with grade 1 mobility and swelling in the buccal vestibule. Vitality tests showed no response to cold and electric pulp testing. The diagnosis of acute apical periodontitis was made on the basis of clinical and radiographic examinations. Hence, treatment advised was root canal treatment. Radiographic evaluation revealed an unusual complex root canal anatomy which showed the presence of two roots with periapical radiolucency. Panoramic x rayClose look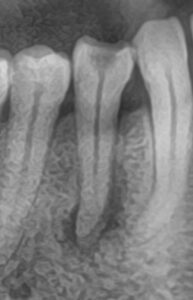
Treatment Procedure
Conventional root canal therapy was planned for the tooth 44. Patient was informed regarding the treatment plan and the unusual root canal anatomy and the complexity involved with it.- Local anesthesia (2% Lidocaine with1:80,000 adrenaline) was administered to achieve profound numbness in the affected region
- A rubber dam was placed to isolate the operative field and maintain an aseptic environment
- Access was gained after complete excavation of caries, ensuring proper visualization, with a long shank straight bur and accessed towards the pulp chamber after under rubber dam isolation.
- To gain sufficient access to the canals, the conventional access opening was modified into one that was wider mesio distally also using endodontic ultrasonic tips acteon ET 18 D.
- Tactile examination of the walls of major canals was done with a small precurved pathfinder file (Dentsply, Maillefer, USA) which was advanced slowly down each wall of the major canal, probing for a catch.
A lateral lesion also signified presence of extra canal or lateral canal. - Initially two root canal orifices were found. To my surprise, one major buccal canal was located very easily with a no. 10 K file.
- Lingual canal was difficult to locate.
- A no. 10 K file was used to locate the lingual canal.
- Finally the third canal was located by scouting.
- The buccal canal was splitting into two at the apex. Hence, the third canal was searched and located through buccal canal orifice which was placed buccolingually with much difficulty.
- Magnification was important because in this case we wanted to locate the direction due to deep split. Orifices were located under magnification using an operating microscope (Labomed Prima) and patency was ascertained with a small size 10 K-file (Mani).
- The working length radiograph was taken.
Type V root canal configuration was seen with the buccal canal.Preparation
- Canals were prepared using Endostar Azure files till 25.04 for major buccal and lingual , later shaped till S2 (Protaper Gold,Dentsply, Maillefer, USA).
- For curved buccal canal – shaping was done til 20.04 file (Azure files, Endo star).
- These canals were sequentially copiously irrigated using 3 % NaOCl and saline.
- Calcium hydroxide (Ultracal,Ultradent) was used as an intra-canal medicament and the access cavity was sealed with IRM between appointments.
Second appointment
- In the next visit after 8 days, the tooth was asymptomatic and thus, we proceeded towards obturation.
- After thorough cleaning, the canals were dried using paper points.
- Obturation was done using a bioceramic sealer (Ceraseal, Meta biomed) and single cone 25.04 GP for buccal and lingual canals.
- Following obturation, coronal sealing was achieved with composite restoration
- Postoperative radiographs were taken to verify the quality of obturation and confirm adequate root filling length.
- Slight sealer was extruded, which was acceptable as per the difficulty level of this case.
- The patient was prescribed analgesics and antibiotics if necessary, and postoperative instructions were provided.
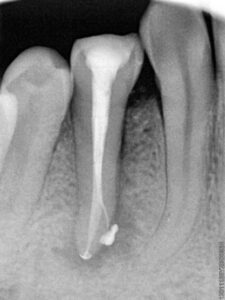 Patient was recalled for regular follow up
 Follow for more such clinical cases onINSTAGRAM - https://www.instagram.com/rootcanalwhisperer1/LINKEDIN - www.linkedin.com/in/dr-disha-gupta-b8009553
Free for members
Keep reading — it's free
The rest of this article is open to DentalReach members. Create a free account, or sign in, and every article on the site opens in full.
