- Dr Disha Gupta, Dubai
Abstract
Extraoral sinus tracts of dental origin continue to be a diagnostic challenge. They are frequently misdiagnosed as lesions of non-odontogenic origin. This is a case report of a patient complaining of extraoral draining sinus since 6 months who visited many medical practitioners. Radiographical investigation showed large periapical lesion associated with root canal treated mandibular 1st molar. Chronic infection of a tooth can drain through a sinus tract, which may be intra-oral or extra-oral. Dental symptoms are not always present or may be missed by patient and this confuses the clinical picture. which can lead to misdiagnosis of the current condition. Timely dental treatment can resolve the condition and with this case report, we can highlight the importance of dental consultation in these situations.
Introduction
A sinus tract is a communication between an enclosed area of inflammation/infection to an epithelial surface or body cavity. The main etiology of extraoral sinus tracts is chronic dental infection. As a result of misdiagnosis, patients may be subjected to unnecessary and ineffective treatment such as repeated courses of antibiotics, multiple biopsies, and surgical excision of the cutaneous lesion. This brings only a temporary resolution of the lesion and once the effect is gone, it reoccurs. When the source of odontogenic infection is eliminated, healing of the sinus is expected within 7 to 14 days.
Clinical presentation of an extra oral sinus - The extra-oral draining sinus typically presents as an erythematous nodule with crusting or ulcer over the skin which drains pus periodically. It is characterized by 'dimpling' or retraction below the normal skin surface. It is usually possible to palpate a cord-like tract that attaches to the underlying alveolar bone in the area of the suspected tooth. Symptoms from the teeth may only present in 50% of patients, the involved tooth is always non vital but may not always be tender to percussion.
This is a case report of a patient complaining of extraoral draining sinus since 6 months who visited many medical practitioners. Timely dental treatment resolved his condition.
Case Report
A 15 year old boy reported with the chief complaint of pus discharge from the right lower jaw region since 6 months reported to the clinic. A draining sinus tract was present extra orally (Fig 1).

For the treatment of extra oral abscess, the patient visited many dermatologists. Initially, the condition was misdiagnosed as infected sebaceous cyst. Antibiotics were prescribed followed by incision and drainage. Even after 6 months, the drainage could not be controlled.
Meanwhile patient was scheduled for pending orthodontic braces consultation. Intra orally, there was a grossly decayed mandibular right first molar tooth with grade 1 mobility & fractured restoration. Periodontal probing around the tooth revealed pocket depth within physiological limits with no intraoral sinus. Radiographic evaluation (panoramic and intra oral periapical) and sinus tracing (x-ray) revealed associated periapical infection of root canal treated right mandibular first molar along with missed mesial canals and short obturation in distal canal (Fig 2a, Fig 2b). TOP test was negative. Dental history revealed that RCT was performed 3-4 years back.


Diagnosis
The differential diagnosis for this case was:
- previously RC treated tooth with chronic apical abscess and extra oral sinus tract
- osteomyelitis
- actinomycosis
- foreign body
- local skin infection
- pyogenic granuloma,
- salivary gland and duct fistula
- suppurative lymphadenitis and
- neoplasm among others.
Based on the clinical and radiographic examinations, a final diagnosisof previously RC treated tooth with chronic apical abscess and extra oral sinus tract was made.
Nonsurgical re-endodontic treatment of the tooth was scheduled.
Treatment
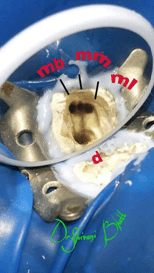
Patient was scheduled for Re-RCT of mandibular 1st molar. Decoronation was done followed by removal of gutta percha from mesial and distal canals. Five root canals, namely the mesiobuccal (MB), mesiolingual (ML), distobuccal (DB), distolingual (DL) and the quite rare mid mesial (MM) canal, were located under a dental operating microscope (DOM) (Fig 3).

Mid mesial canal plays a very important role in these cases, one missed canal can further complicate the case and leads to non-healing of the extra oral sinus along with periapical lesion.
Chemo mechanical preparation done using saline, 3 % NaOCl and 0.2% chlorhexidine digluconate solution (after thoughly flushing the canals with saline or water). Canals were then shaped using Protaper Gold files. The canals were then dressed with water based calcium hydroxide paste (Ultracal). Cleaning, shaping and filling of the root canal and periradicular region determine the success of the treatment and good periradicular healing. The sinus tract was treated with H2O2 irrigation along with povidine iodine solution to remove the dead necrotic tissue of the tract and facilitate healing.
Patient was recalled after two weeks, no more suppuration from the sinus tract was observed with spontaneous closure of the tract (Fig 4).

The interim dressing was changed every two weeks for 2 months. During this period, the patient remained asymptomatic; meanwhile upon radiographic investigation the periapical area showed signs of excellent healing and bony recovery. Subsequently, the root canal obturation with gutta-percha points and bio ceramic sealer was performed (Fig 5).

Discussion
Sinus Tracts
A sinus tract prevents swelling or pain from increased pressure because it provides drainage from the primary odontogenic site. Symptoms from the teeth are present only in 50% of patients, which could explain why patients frequently consult with a physician first for help. Mostly in such cases, delay in the diagnosis often leads to unnecessary antibiotic treatment and surgical intervention. Intervention must start with an intensive medical and clinical history, and odontogenic infection must be borne in mind in the differential diagnosis of such lesions on the face or neck. Hence, the clinician should pay extraordinary attention to oral clinical conditions, such as caries, deficient restorations, and periodontal conditions.
How do extra -oral sinus tracts form? - Sinus tracts of dental origin may be misdiagnosed due to lack of dental history provided by patient. If a draining lesion is seen on the facial or cervical area, a dental origin should be considered a priority in differential diagnosis. Other etiologies consist of pyogenic granuloma, foreign body reaction, deep fungal infection, squamous cell carcinoma, and osteomyelitis. Odontogenic cutaneous sinus tracts typically arise from periapical infections around the root apices as a result of pulpal necrosis, nearby caries or traumatic injury. This chronic process slowly evolves through the cancellous alveolar bone, following the path of least resistance until it perforates the cortical plate of the mandible. Cutaneous fistulas then arise from the spread of infection into the surrounding soft tissues. Sometimes the location of the sinus tract opening does not necessarily indicate the origin of the inflammatory exudate, tracking of the sinus tract with a gutta-percha point contributes to the final correct diagnosis.
Free for members
Keep reading — it's free
The rest of this article is open to DentalReach members. Create a free account, or sign in, and every article on the site opens in full.