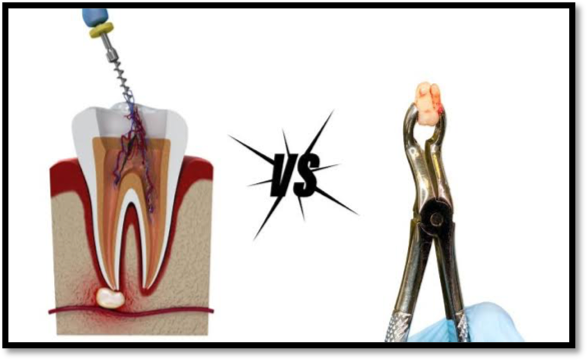
Does Every Root Canal Tooth Need a Crown?
Modern evidence has moved on from the automatic post-and-crown pairing. Here is what the science actually says — and how to make the right decision for your tooth.
GS
Dr. Gautam Shetty, MDS Endodontist
·Redefine Dental Clinic, Kalyan West·2026
Not always. For decades, the default treatment after a root canal has been a post and full-coverage crown. Modern evidence shows that whether your tooth needs a crown depends far more on how much healthy structure is left — than on the root canal itself.
If you've recently had a root canal, or your dentist has told you that you will need one, there's a good chance you've also been told you need a crown to follow.
It's such a routine recommendation that most patients don't think to ask why. The procedure has been packaged as a single treatment plan for as long as anyone can remember. Drill the canal, fill it, top it with a crown.
What if the science has moved on from that automatic pairing?
Modern restorative dentistry now recognizes something the older textbooks underplayed. Whether your tooth survives long term doesn't actually depend on the root canal itself. It depends on how much healthy tooth structure is still standing after the decay, fracture, or trauma that brought you to the dentist in the first place.
This shift has a name. Biomimetic dentistry. And it's quietly changing how thoughtful clinicians think about post-root-canal care.
◆
The old rule —and why it's outdated
For most of the last fifty years, dental schools taught a binary. Endodontically treated tooth equals post and crown. The reasoning was that root-filled teeth become brittle without their pulp, and that the only safe way to protect them was full coverage.
Decades of clinical research have complicated that picture. Studies have repeatedly shown that the loss of vitality alone has a relatively minor effect on tooth strength. What dramatically reduces strength is the loss of healthy tooth tissue — which has often already happened by the time someone needs a root canal in the first place.
Two numbers from biomechanical research illustrate the point:
5%
Loss of cuspal stiffness when only the access cavity is lost
46%
Loss of strength when a marginal ridge is lost due to decay or fracture
Same procedure underneath. Wildly different teeth. Wildly different treatment plans should follow.
The ferrule —the most important measurement most patients have never heard of
If you walk away from this article remembering one new word, make it ferrule.
Key Concept
What is the ferrule?
The ferrule is a1.5 to 2mm band of healthy dentin that wraps the base of your tooth like a collar, just above the gum line. It's what gives a restoration something to grip onto. It distributes biting forces. It is the single strongest predictor of whether your restored tooth holds up over the long term.
If your ferrule is at or above 1.5mm, conservative restorations have excellent fatigue resistance. Composites bond well, onlays seat properly, and even crowns last longer because they have a stable foundation.
If your ferrule is under 1.5mm, the picture changes. No post, no crown, no high-end material can fully compensate for the lack of healthy structure to anchor against. In those cases, your dentist should be talking to you about crown lengthening or orthodontic extrusion before placing a post.
A good consultation will involve someone actually showing you what your ferrule looks like on imaging. If that part of the conversation is missing, it is worth asking.
"The right question isn't whether root canal teeth need crowns — it's what does this particular tooth need, given what's actually left of it."
What actually decides your treatment plan
The most current research suggests a decision framework that depends on three things: which tooth, how many walls of the tooth are still intact, and whether you grind your teeth.
Treatment decision framework — by tooth type & remaining structure
Tooth Type
Walls Intact
Recommended Option
Front teeth (incisors / canines)
3 – 4 walls
Direct composite
Front teeth (incisors / canines)
1 – 2 walls
Post + Crown
Back teeth (premolars / molars)
3 – 4 walls
Composite or bonded onlay
Back teeth (premolars / molars)
Free for members
Keep reading — it's free
The rest of this article is open to DentalReach members. Create a free account, or sign in, and every article on the site opens in full.