
Full mouth rehabilitations (FMR) are comprehensive dental procedures aimed at restoring optimal oral health and function in patients with extensive dental issues. It is considered when a patient presents with a complex set of dental problems that cannot be effectively addressed through isolated treatments. Common scenarios include severe tooth wear, advanced periodontal disease, widespread decay, and multiple missing teeth, affecting their phonetics, esthetics and functional occlusion. Additionally, individuals with temporomandibular joint (TMJ) disorders or occlusal problems may benefit from full mouth rehabilitation to restore harmony in their bite and alleviate associated symptoms. But there is another type of rehab, which addresses only selective issues of functional occlusion and is certainly not as inclusive as a traditional FMR, referred to as a ‘selective rehab’. Selective rehabs are sometimes frowned upon and are considered controversial in nature, because: 1) It’s a compromised treatment plan, which does not address all dental issues simultaneously. 2) It may or may not prevent the progression of existing problems and the development of new ones. 3) It may or may not contribute to the long-term stability of the patient's oral health. That said, there is a small segment of patients who do not fit in the scope of a typical full mouth rehab. These patients show selective wear of teeth, usually on one side only, i.e. only two quadrants rather than four. The reasons for this usually are- 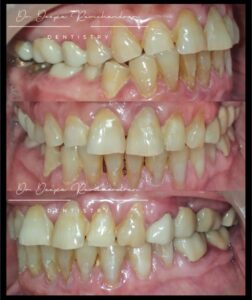
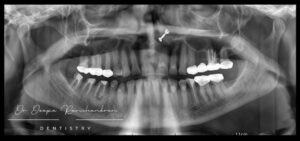 The pre-operative images and OPG show:
- previous prosthesis fabricated in a wrong plane of occlusion or
- unilateral mastication by the patient eventually leading to damage of the existing prosthesis.
How is Selective Full Mouth Rehabilitation Performed?
1) Thorough Assessment: The process begins with a comprehensive assessment of the patient's oral health. This includes a detailed examination, diagnostic imaging (such as an OPG), and discussions about the patient's concerns and goals including their monetary constraints. 2) Treatment Planning: Based on the assessment, a customized treatment plan is developed, which is usually limited to only one side or two quadrants. The treatment plan may include a combination of restorative, periodontal, endodontic, and prosthetic procedures. 3) Phased Approach: Selective rehabs themselves can be considered as a form of phased dental treatment, allowing the dentist to prioritize and address immediate concerns first rather than potential future ones. 4) Collaboration between Specialists: Some cases may involve collaboration between different dental specialists, such as prosthodontists, periodontists, oral surgeons, and orthodontists. This interdisciplinary approach ensures that each aspect of treatment is expertly handled. 5) Provisional Restorations: Temporary or provisional restorations are placed during the treatment process to maintain function and esthetics while the final restorations are being fabricated. This step is especially important to evaluate the restored functional occlusion and the patient’s adaptation to it. 6) Final Restorations: Once all necessary procedures are completed, final restorations are placed. This may include crowns, bridges, dental implants, or other prosthetic devices to achieve the desired functional and aesthetic outcomes. I would like to illustrate the above aspects in the form of a case report.Case Report
A lady in her early seventies entered my operatory with dislodged crown prostheses on 47 and 48 along with the chief complaint of being unable to masticate. She was referred by another clinician to me, specifically for a selective rehab. The pre-operative images and OPG show: - loss of vertical dimension on the right with a complete reverse Curve of Spee.
- loss of soft and hard tissue on the lower incisors.
- grade 1 mobility on 31 and 41; trauma from occlusion.
- attrition on the incisal edge of anteriors (i.e.lack of anterior guidance).
- various cervical abrasion defects.
- uneven zenith and shade mismatch of UL FPD.
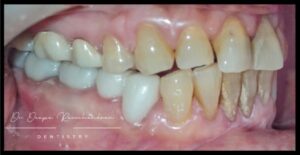 The LR final prosthesis was then cemented.
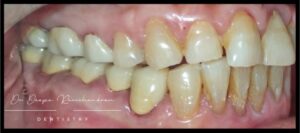 Next, 12 and 13 were prepped for full coverage zirconia crowns, to enable me to change the palatal contour. A before and after comparison, shows us the corrections in functional occlusion especially with respect to the plane of occlusion. Note the beautiful gingival adaptation around the LR FPD.
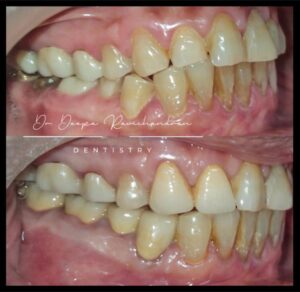 In conclusion, the decision to pursue selective rehabilitation involves a thorough assessment, careful treatment planning, and patient co-operation to ensure effective and manageable care. It is also deceptively more tedious, time consuming and technique sensitive, than it appears, and requires the clinician to have a very through knowledge of functional occlusion, especially as, drastic corrections have to be brought about, but within pre-existing parameters. This necessitates that the clinician understand, that while ideal restoration of occlusion is not possible, every effort must be made to achieve the maximum corrections, within the framework of a selective rehab.
Free for members
Keep reading — it's free
The rest of this article is open to DentalReach members. Create a free account, or sign in, and every article on the site opens in full.
